ARFID Diagnostic Criteria and Why the Diagnosis Is Often Missed


- ARFID is an eating disorder that can affect how much someone eats, the variety of foods they eat, or both. Providers use specific criteria to understand whether these patterns meet the requirements for a diagnosis.
- ARFID can affect people of any age or body size. You don’t have to be underweight for your eating difficulties to deserve attention or support.
- With ARFID, food restriction isn’t driven by a desire to lose weight or change body shape. Instead, sensory sensitivities, low interest in food, or fear can make eating difficult.
- People sometimes mistake ARFID for picky eating or another condition. An assessment that considers physical health, nutrition, and mental health can help you understand what’s happening and find the right care for your patient.

“Just try one bite.” “Eat when you’re hungry.” “You’ll grow out of it.” People who struggle with eating may hear this advice often. But when textures feel overwhelming, hunger rarely shows up, or eating causes fear, there may be more going on. Enter the ARFID diagnostic criteria, which help providers recognize when these eating difficulties signal an eating disorder.
Avoidant/restrictive food intake disorder (ARFID) is an eating disorder in which someone limits how much they eat, their food variety, or both, according to Pediatric Reviews. It can affect people of any age or body size and often goes unrecognized.
“One main reason ARFID is often misdiagnosed or missed entirely is because it's a relatively new diagnosis,” says Sam Bender, LCSW-S, lead therapist at Equip.
The ARFID diagnostic criteria in the DSM-5-TR help clarify when eating challenges meet the definition of this disorder. Whether you’re seeking answers for a patient, loved one, or yourself, here’s how ARFID is diagnosed, why ARFID gets missed, and what an assessment involves.
What are the diagnostic criteria for ARFID?
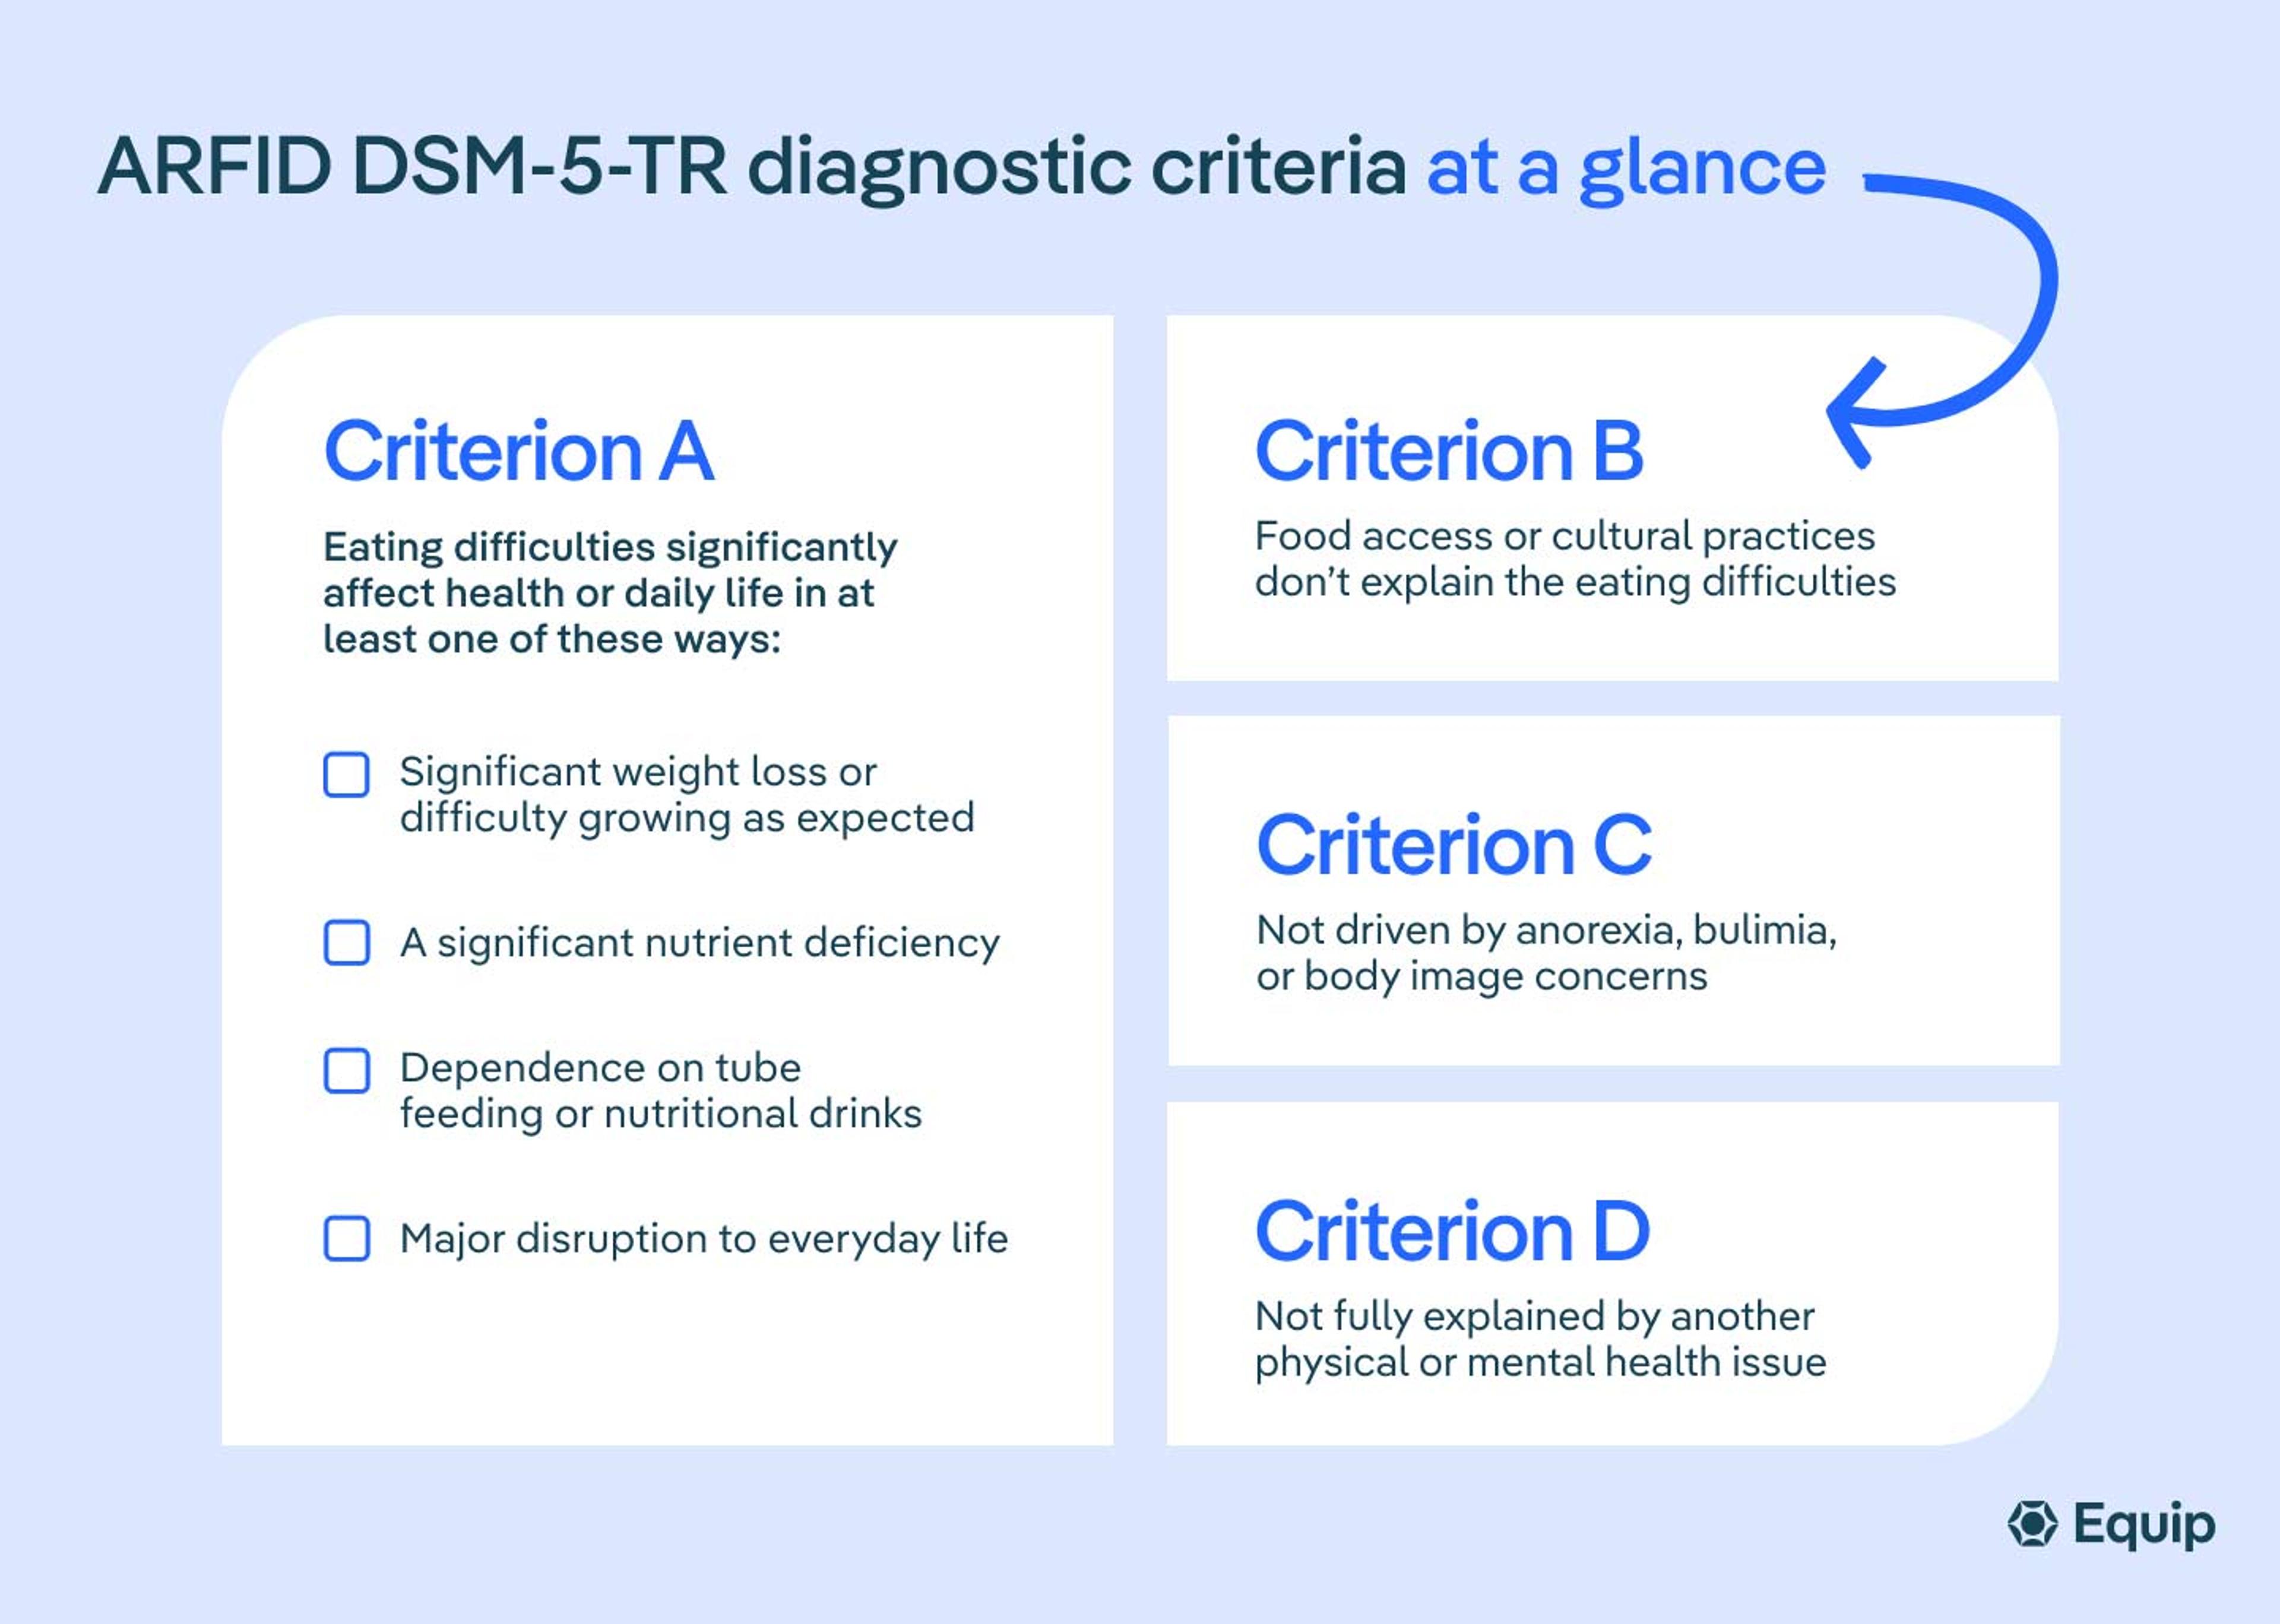
ARFID is diagnosed when eating difficulties significantly affect someone’s health or daily life and meet the following four DSM-5-TR criteria:
- Criterion A: Eating difficulties significantly impact daily life. Someone may lose weight, struggle to grow as expected, miss out on important nutrients, rely on a feeding tube or nutritional drinks, or find that eating difficulties get in the way of everyday functioning.
- Criterion B: Lack of access to food or a cultural or religious practice doesn’t explain the eating pattern.
- Criterion C: Anorexia or bulimia don’t fully explain the eating difficulties, and concerns about body image don’t drive the eating behaviors.
- Criterion D: Another physical or mental health condition doesn’t fully explain the eating difficulties, either. If someone has another condition, their struggles with eating go beyond what’s usually expected with it and need attention of their own.
The core criterion (Criterion A)
Criterion A focuses on how eating difficulties affect someone’s health and daily life. Providers look for at least one of these four consequences:
- Significant weight loss or failure to grow as expected: For a child, this can mean falling behind their expected pattern of weight gain or growth.
- A significant nutritional deficiency: Providers review someone’s eating patterns and may order blood tests to check for nutrient gaps that aren’t obvious based on weight or appearance.
- Dependence on tube feeding or nutritional drinks: Some people with ARFID may rely on these to meet their nutritional needs.
- Major disruption to everyday life: Eating difficulties may make it hard to participate in school, work, relationships, or social activities. For example, someone might regularly miss gatherings because they feel too distressed to eat around others.
Hands on resources for patients and families
The exclusion criteria (Criteria B-D)
“Providers consider food insecurity, cultural practices, medical conditions, medication side effects, and other potential factors during the assessment to ensure another condition doesn't better explain the eating disturbances,” Bender says.
Here’s what that looks like in practice:
- Criterion B asks whether someone has enough food available and whether cultural or religious practices explain their eating pattern. Limited food access, for example, calls for support with getting enough food rather than an ARFID diagnosis based on that restriction alone.
- Criterion C helps providers distinguish ARFID from anorexia and bulimia. They ask whether concerns about weight or body shape drive the restriction and whether the eating difficulties occur only in the context of one of those other eating disorders.
- Criterion D asks whether another physical or mental health condition fully explains the difficulties. For instance, a digestive condition might make eating physically painful and call for targeted gastrointestinal care. That said, having another condition doesn’t rule out ARFID. For example, someone with celiac disease needs to avoid gluten; but if fear of getting sick also leads them to avoid many foods they can safely eat, a provider may assess for ARFID too (in fact, there is a documented link between food allergies and ARFID).
How ARFID differs from picky eating and other eating disorders
The main differences between ARFID, picky eating, and other eating disorders come down to what makes eating difficult and how much it affects someone’s life. Picky eating can cause stress, but ARFID involves significant consequences for health or daily activities. And unlike anorexia and bulimia, weight or body image concerns don’t drive the restriction.
Here’s the breakdown:
- ARFID vs. picky eating: Picky eaters generally have enough flexibility to get the nourishment they need, even if trying new foods feels challenging. With ARFID, eating difficulties persist and significantly affect nutrition, growth, or everyday activities.
- ARFID vs. anorexia nervosa: Both can involve eating too little, but the reasons differ. With anorexia, fear of weight gain and concerns about body image play a central role, per the Avicenna Journal of Medicine. With ARFID, the difficulty comes from the food or eating experience itself. Providers often describe three ARFID presentations: sensory-based avoidance; low interest in food or eating; and fear of choking, vomiting, or other consequences.
- ARFID vs. bulimia nervosa: Bulimia involves recurring episodes of binge eating followed by behaviors like vomiting or fasting to prevent weight gain, according to the journal Focus. With ARFID, body image concerns don’t drive eating behaviors, and the disorder does not include weight control behaviors.
- ARFID vs. medical causes of restricted eating: Someone might eat less because of a food intolerance or because a health condition makes eating painful or swallowing difficult, or causes nausea. That alone doesn’t mean they have ARFID. But if they also avoid foods they can safely and comfortably tolerate, a provider may assess for ARFID too.
- ARFID vs. pediatric feeding disorder: Pediatric feeding disorder involves difficulty with the mechanics of eating, like chewing or swallowing. With ARFID, a child may have those skills but struggle to eat because textures feel overwhelming or food holds little interest.
Across these comparisons, it’s important to remember that body size doesn’t tell the whole story. ARFID affects people of all body sizes, and someone doesn’t have to be underweight to meet the diagnostic criteria or need support.
If you’re concerned a patient may have ARFID, Equip’s clinically validated ARFID screener can help you determine if ARFID may be present.
ARFID | Picky eating | Anorexia nervosa | |
What drives the restriction | Sensory sensitivities, low interest in eating, or fear of choking, vomiting, or other consequences | Food preferences and reluctance to try unfamiliar foods | Fear of weight gain |
Role of body image | Weight or body shape concerns don’t drive food avoidance | Weight or body shape concerns generally don’t drive food preferences | Weight and body shape strongly influence eating behaviors |
Typical course | Difficulties persist/worsen without care, but recovery is possible. ARFID may begin in childhood or later in life | Often becomes more flexible with time, though preferences can persist | Can persist or worsen without care; recovery is possible |
Effects on nutrition and health | Can affect growth, cause nutrient deficiencies, or lead to reliance on nutritional drinks or tube feeding; low weight isn’t required | Generally allows enough food and variety to support nutrition and growth | Restriction leads to significantly low weight and can cause serious medical complications |
Effects on daily life | May substantially limit school, work, relationships, or activities involving food | Can make meals stressful, but usually allows participation in everyday activities | Food rules, weight concerns, and effects of undernourishment can disrupt everyday life |
Need for treatment | Needs specialized assessment and eating disorder care | Often responds to supportive guidance | Needs specialized assessment and eating disorder care |
Why ARFID is often missed or misdiagnosed
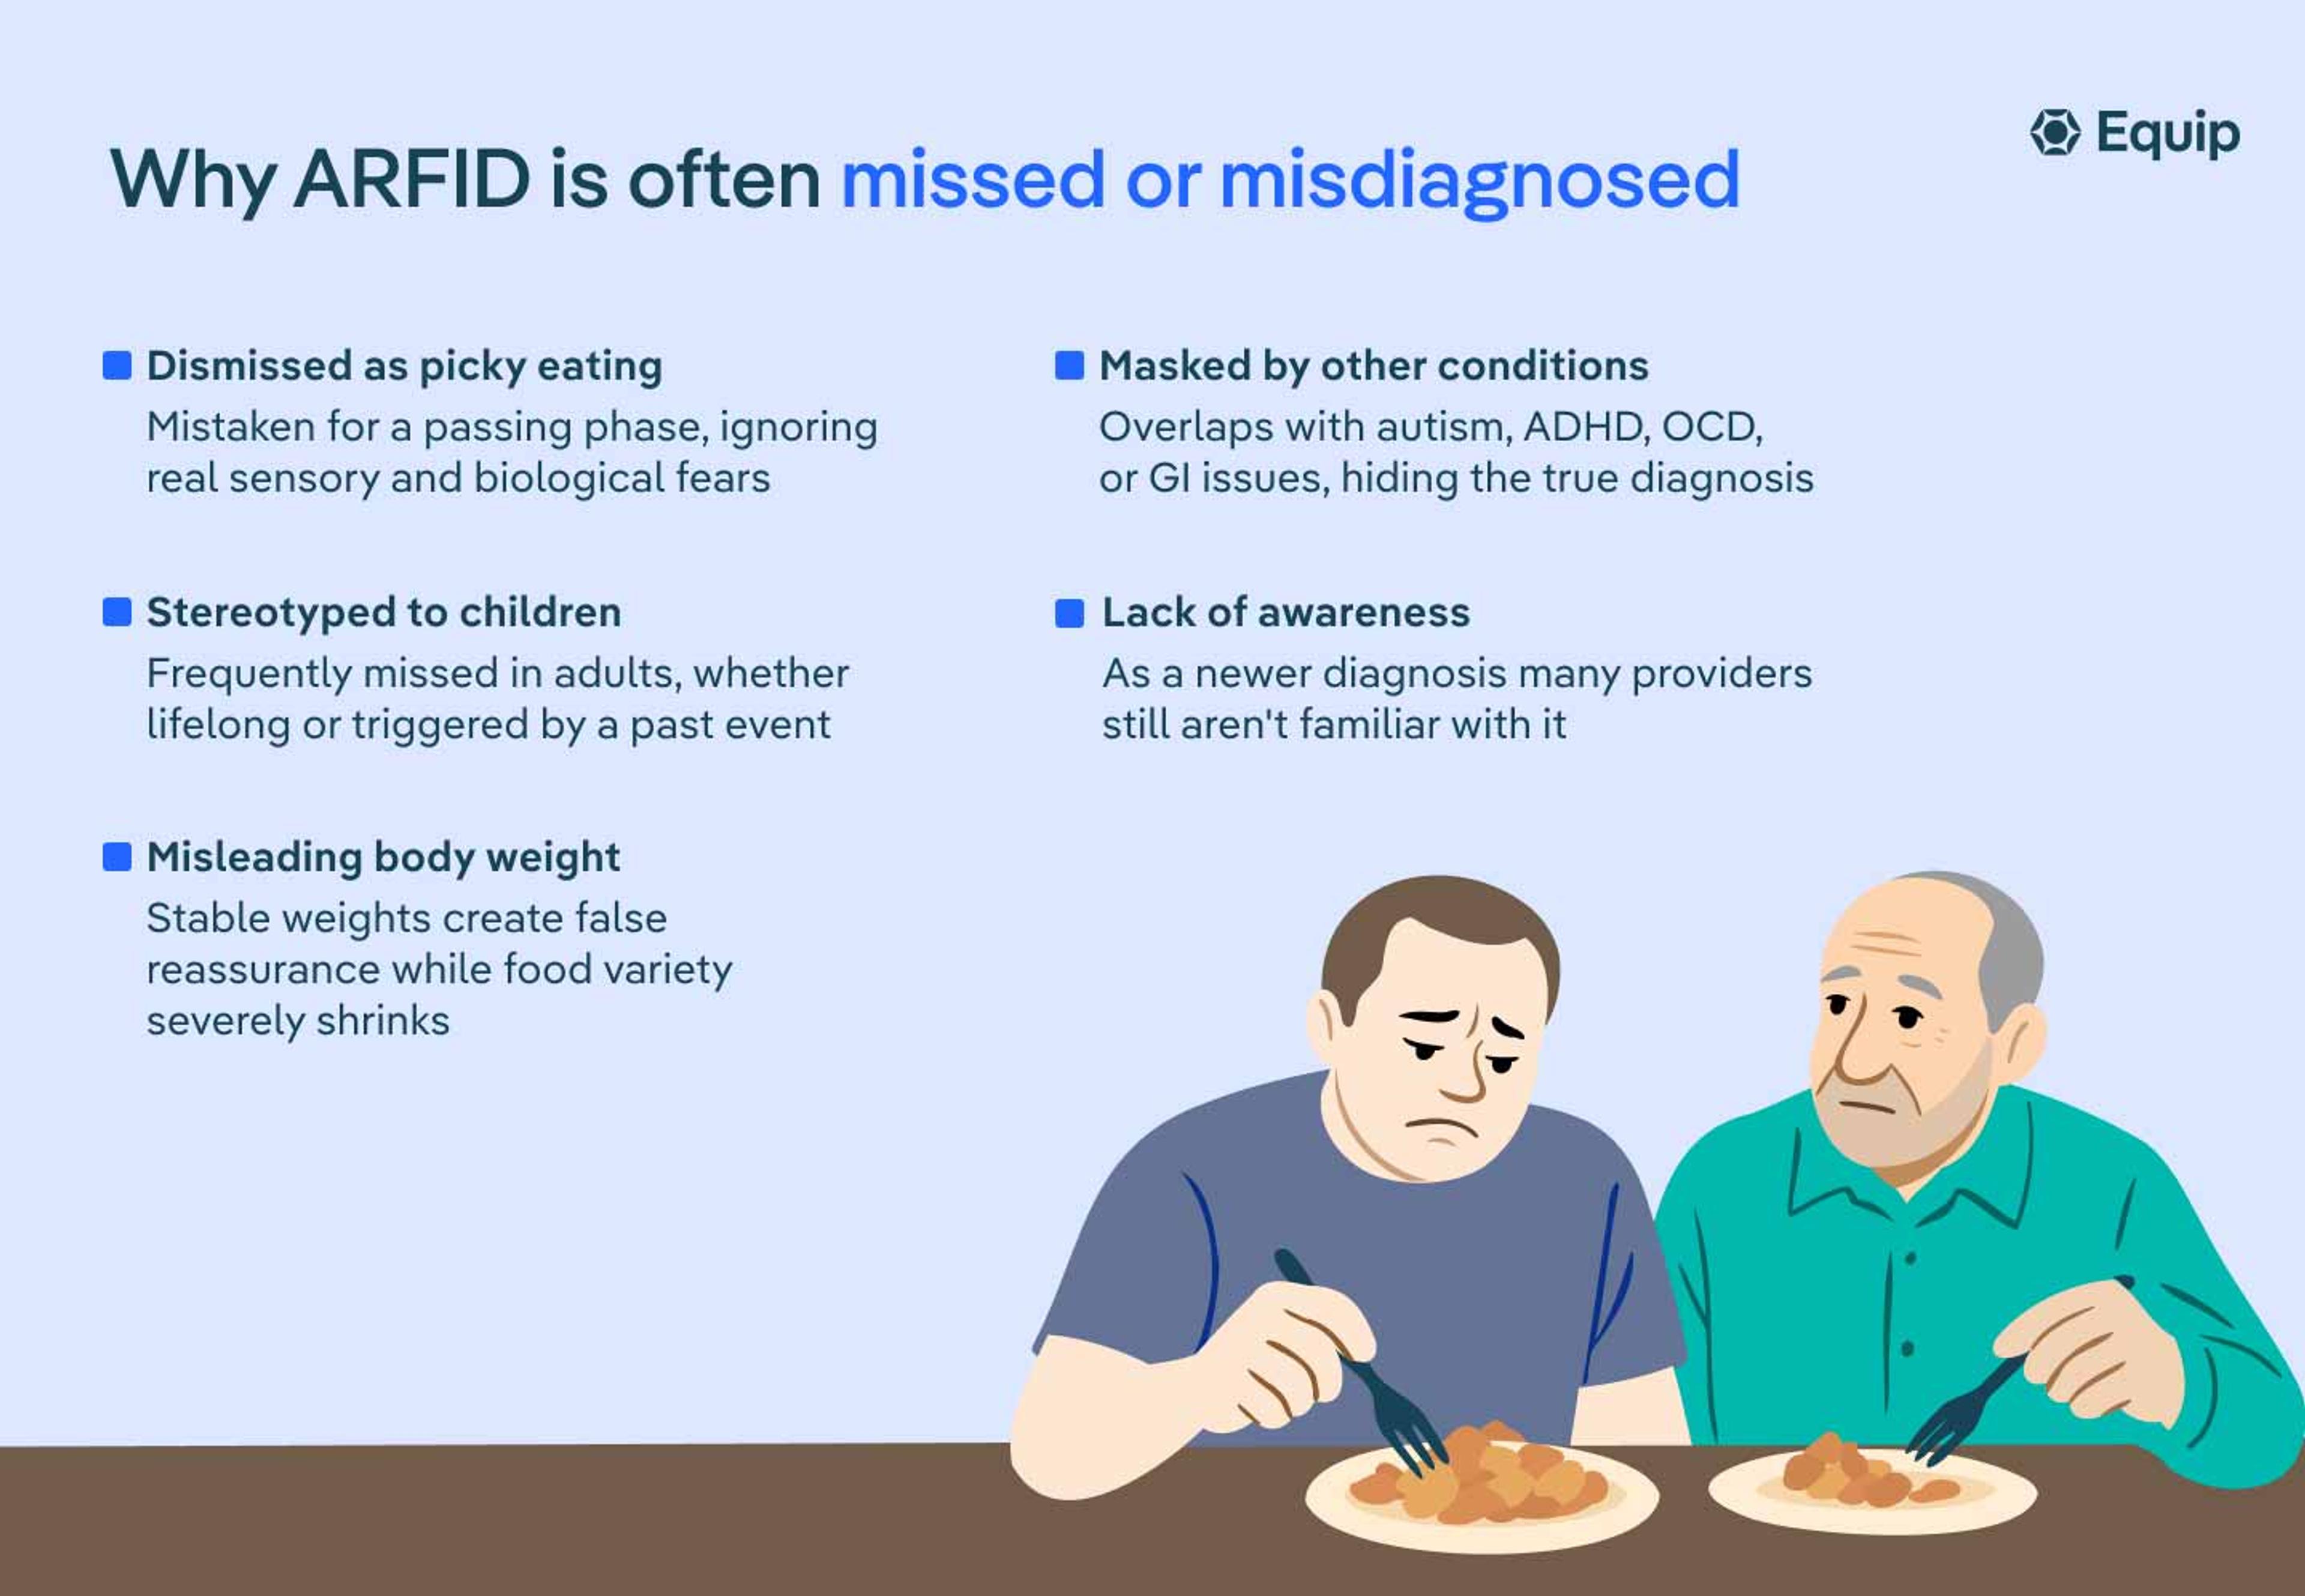
ARFID often goes unrecognized because people mistake it for picky eating, attribute eating difficulties to another condition, or assume eating disorders only affect children or people in smaller bodies.
For someone living with ARFID, that can mean years of trying to manage meals without understanding why eating feels so hard. According to Bender, several factors can keep them from getting answers:
- People expect them to grow out of it: “Parents may assume their child is picky or going through a phase, but ARFID goes far beyond picky eating and food preferences,” says Bender. “People with ARFID often have biological reasons for a lack of interest in food or sensitivity to sensory experiences, and they may experience real fear about certain foods or settings.”
- Another diagnosis gets all the attention: ARFID and OCD, autism, ADHD, anxiety disorders, and gastrointestinal conditions all have overlapping symptoms and can even occur at the same time, per StatPearls. This can cause ARFID to be overlooked. For example, a provider might attribute a child’s shrinking food variety to autistic sensory sensitivities without considering that ARFID may also be at play.
- Adults don’t fit the expected picture: Some adults have struggled with eating since childhood without knowing why. Others develop difficulties later, sometimes after a scary experience like an allergic reaction. Either way, providers may miss ARFID in adults if they only associate it with children.
- Weight creates false reassurance: A person’s weight may stay stable even when their food options become increasingly limited or eating takes over their daily routine. Providers who look only for low weight can miss ARFID in people at typical weights or in larger bodies. Asking about food variety, distress, and daily life helps reveal what a weight measurement can’t.
- Many people still aren’t familiar with ARFID: ARFID wasn’t an official diagnosis until it entered the DSM in 2013. “This means many people, including providers, may not be familiar with ARFID and may look towards more familiar diagnoses when trying to explain what's occurring,” says Bender.
A patient may have felt that their concerns were dismissed before, and it’s important they not feel they should manage this alone. Having them describe what makes eating difficult—and what they miss out on or struggle with because of it—can be a productive way to help them understand why a closer look matters.
What an ARFID assessment involves
An ARFID assessment explores someone’s eating history, physical health, nutrition, and mental health to understand what makes eating difficult and whether they meet the diagnostic criteria. Importantly, someone does not need to know why they’re struggling before reaching out. The assessment is meant to give someone space to describe their experiences and help providers put the pieces together.
“A multidisciplinary approach to ARFID assessment is the gold standard,” Bender says. That means providers with different areas of expertise work together to understand someone’s needs. Depending on the situation, a therapist, dietitian, and specialist (like a gastroenterologist and/or psychiatrist) may all be involved in treatment.
According to Bender, diagnosing ARFID typically involves evaluating different factors, including::
- A patient’s experiences with food: A provider looks for signs of ARFID by talking through which foods the patient can comfortably eat, what feels difficult, and when those difficulties started. They may ask whether food options have narrowed over time or whether a particular experience changed how someone feels about eating. They also explore how meals affect school, work, relationships, and routines.
- A patient’s physical health: A medical provider reviews health history, checks vitals, and considers blood tests to look for nutritional deficiencies or other concerns. They ask about symptoms like pain, nausea, or trouble swallowing and review medications that might affect appetite. For ARFID in children and teens, they also look at growth over time.
- A patient’s eating patterns and nutritional needs: A dietitian explores what a patient eats and drinks, how consistently they can eat, and whether they rely on nutritional drinks or other support. This helps identify possible nutrient gaps, even when someone’s weight hasn’t changed.
- A patient’s mental health and development: A therapist asks about fear, sensory sensitivities, interest in food, and any weight or body image concerns. They also consider conditions like anxiety, OCD, autism, or ADHD that might help explain a patient’s experiences or shape the care you need.
“Together, the team can create a clearer picture of what the patient is experiencing and decide on the best course of ARFID treatment,” Bender says.
Providers can also refer a patient to Equip for specialized, multidisciplinary ARFID care. Equip’s team works with you and the patient’s other providers to coordinate their treatment every step of the way.
The bottom line
The ARFID diagnostic criteria give providers a clear framework for diagnosis. Recognizing the disorder means looking beyond someone’s weight or the foods they avoid to understand what makes eating difficult, how those difficulties affect their life, and whether another condition explains them.
For people who have heard that they’re “just picky” or should try harder, that understanding can matter. Eating difficulties deserve attention at any age or body size, and a thorough assessment can help your patients find care that fits their needs. With the right support, people with ARFID can expand the foods they eat, meet their nutritional needs, and feel more comfortable participating in everyday life.
FAQ
What tests are done for ARFID?
Providers use interviews, questionnaires, a health review, and sometimes blood tests to assess for ARFID. No single test can confirm the diagnosis. Blood tests can help identify nutrient deficiencies or other health concerns, while conversations about eating help providers understand what makes food difficult and how it affects a patient.
Is ARFID in the DSM-5?
Yes, ARFID first appeared in the DSM-5 in 2013 and remains in the updated DSM-5-TR.
Can adults be diagnosed with ARFID?
Yes, adults can receive an ARFID diagnosis, whether their eating difficulties began in childhood or developed later. Some adults have spent years adapting their routines around food without realizing they could benefit from support. That’s why it’s worth seeking an assessment even if these patterns feel familiar or longstanding.
- Matheson, Brittany E. “Bulimia Nervosa and Binge-Eating Disorder Across the Lifespan.” Focus (American Psychiatric Publishing) vol. 22,3 (2024): 278-287. doi:10.1176/appi.focus.20240001
- Nagy, Hassan et al. “A Clinical Overview of Anorexia Nervosa and Overcoming Treatment Resistance.” Avicenna journal of medicine vol. 13,1 3-14. 21 Dec. 2022, doi:10.1055/s-0042-1758859
- Ramirez, Zerimar, and Sasidhar Gunturu. “Avoidant Restrictive Food Intake Disorder.” Nih.Gov, StatPearls Publishing, May 2024, https://www.ncbi.nlm.nih.gov/sites/books/NBK603710/. Accessed 5 Oct. 2026.
- Seetharaman, Sujatha, and Errol L Fields. “Avoidant/Restrictive Food Intake Disorder.” Pediatrics in review vol. 41,12 (2020): 613-622. doi:10.1542/pir.2019-0133








